
Bradycardia in Neonates: Causes and Immediate Management
Neonates and infants frequently respond to stress with bradycardia rather than tachycardia. This article explains the most common triggers (hypoxia, vagal stimulation, medications), critical heart rate thresholds, and the stepwise approach from stimulation to epinephrine administration.

Author: Dr. med. univ. Daniel Pehböck, DESA
Specialist in Anesthesiology and Intensive Care Medicine, AHA-certified ACLS/PALS Instructor, Course Director Simulation Tirol
Reading time approx. 8 min
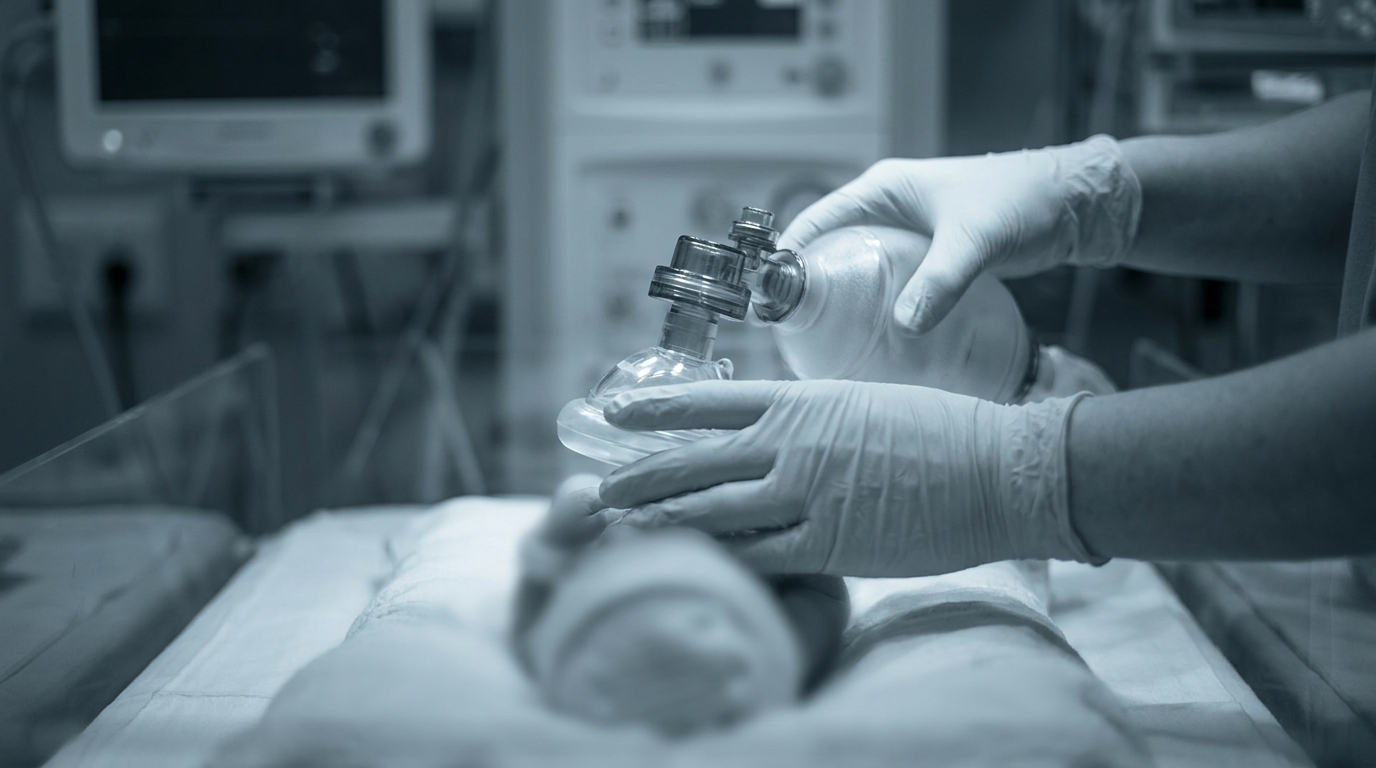
Neonates and infants differ fundamentally from older children and adults in their cardiovascular physiology. While the adult heart typically responds to stress with tachycardia, the primary response of the immature heart to hypoxia, acidosis, or vagal stimulation is frequently bradycardia. This difference has immediate therapeutic consequences: a heart rate below 60/min in a neonate is an emergency requiring immediate, algorithm-based action – not watchful monitoring. Understanding the pathophysiology behind this allows you to recognize the urgency and act faster.
Why Do Neonates Respond with Bradycardia?
The cardiac output (CO) of a neonate is almost exclusively rate-dependent. The myocardial contractility reserve is limited, and stroke volume can barely be increased. A drop in heart rate therefore leads directly and proportionally to a drop in CO and consequently to tissue hypoperfusion.
Parasympathetic Dominance
The autonomic nervous system of the neonate exhibits relative parasympathetic dominance. Vagal tone is high, and sympathetic innervation of the myocardium is still incompletely developed. This means:
- Vagal stimuli (suctioning, laryngoscopy, cold exposure, defecation) can trigger a disproportionately severe bradycardia.
- The sympathetic counter-regulation that rapidly compensates for reflex bradycardia in adults is significantly weaker in neonates.
Hypoxia as the Primary Trigger
By far the most common cause of neonatal bradycardia is hypoxia. The mechanism involves the so-called diving reflex: hypoxia activates peripheral chemoreceptors, which trigger bradycardia and peripheral vasoconstriction via vagal afferents. What serves as a protective function in diving mammals becomes a life-threatening downward spiral in the neonate under pathological conditions:
Hypoxia → Bradycardia → CO drop → Tissue hypoxia → Further bradycardia → Asystole
This vicious cycle explains why the treatment of neonatal bradycardia primarily targets the correction of hypoxia – not pharmacological rate enhancement.
Common Causes in Clinical Practice
Systematic identification of the cause is crucial for targeted therapy. The following overview is organized by clinical frequency:
Respiratory Causes (Most Common Group)
- Apnea – central (prematurity, infection, intracranial pathology) or obstructive
- Airway obstruction – mucus, meconium, malformations (e.g., choanal atresia, Pierre Robin sequence)
- Pneumothorax – particularly after ventilation or resuscitation
- Inadequate ventilation – absent or insufficient bag-mask ventilation, endotracheal tube malposition
- Congenital diaphragmatic hernia – impaired lung function due to displacement of abdominal organs
Cardiac Causes
- Congenital heart defects – structural anomalies with hemodynamic significance
- Congenital AV block – particularly in maternal lupus erythematosus (anti-Ro/SSA antibodies)
- Myocarditis – viral, rarely bacterial
- Pericardial effusion/tamponade – e.g., following central venous catheter placement
Vagally Mediated Bradycardia
- Suctioning maneuvers – particularly deep nasotracheal or pharyngeal suctioning
- Laryngoscopy and intubation – direct vagal stimulation
- Oculocardiac reflex – pressure on the globes (relevant in ophthalmology)
- Defecation and vomiting – Valsalva-associated
Metabolic and Systemic Causes
- Hypothermia – iatrogenic (delivery room!) or from exposure
- Hypoglycemia – particularly in SGA infants and infants of diabetic mothers
- Hyperkalemia – in renal insufficiency, hemolysis, transfusion complications
- Acidosis – respiratory and/or metabolic
- Sepsis – with accompanying myocardial depression
Drug-Related Causes
- Maternal medications – beta-blockers, calcium channel blockers, magnesium sulfate (tocolysis, eclampsia prophylaxis), opioids
- Neonatal medications – succinylcholine (without atropine pretreatment), prostaglandin E1 (maintaining ductal patency in duct-dependent cardiac lesions), dexmedetomidine
Critical Heart Rate Thresholds
Heart rate is the most important vital parameter for assessing the neonatal condition – more important than skin color, muscle tone, or SpO₂ in the first minutes of life.
The AHA guidelines for neonatal resuscitation define the following thresholds:
| Heart Rate | Interpretation | Action |
|---|---|---|
| > 100/min | Adequate | Continue observation, supportive measures |
| 60–100/min | Bradycardia | Ensure effective ventilation, reassess |
| < 60/min despite adequate ventilation | Severe bradycardia | Begin chest compressions |
| < 60/min despite ventilation + compressions | Critical bradycardia/pre-asystole | Epinephrine |
Key point: In the neonate, a heart rate below 60/min is functionally equivalent to cardiac arrest, as CO at this rate is insufficient to maintain adequate organ perfusion.
Stepwise Approach: From Stimulation to Epinephrine
Neonatal resuscitation follows a clear stepwise algorithm. It is essential that each step is performed thoroughly and correctly before escalating to the next. In practice, resuscitation fails more often due to inadequate ventilation than due to the absence of medications.
Step 1: Initial Steps and Tactile Stimulation
- Maintain warmth – Dry the infant, remove wet towels, use a radiant warmer or warming mattress. Hypothermia worsens bradycardia.
- Clear the airway – Head in neutral position (sniffing position), gently suction mouth and nose if needed (caution: excessive suctioning triggers vagal bradycardia!).
- Tactile stimulation – Rub the soles of the feet, stimulate the back. Brief, targeted stimuli. Do not continue futile stimulation repeatedly – if no improvement occurs after 10–15 seconds, ventilation must be initiated.
Step 2: Positive Pressure Ventilation (PPV)
Positive pressure ventilation is the most important and most effective intervention for neonatal bradycardia. In the vast majority of cases, adequate ventilation alone is sufficient to normalize the heart rate.
- Rate: 40–60 breaths/min (corresponding to "breathe-two-three, breathe-two-three")
- Initial pressure: 20–25 cmH₂O for term neonates, potentially lower for preterm infants
- Initial breaths: may require higher pressure (up to 30 cmH₂O) to open fluid-filled alveoli
- FiO₂: Start with 21% (room air) for term neonates, titrate based on SpO₂. For preterm infants < 35 weeks GA, start with 21–30%
- Assessment of effectiveness: Visible chest rise? Heart rate increase within 15–30 seconds?
If the heart rate does not rise despite PPV, systematically reassess ventilation – MR SOPA:
- M – Mask adjustment (correct mask seal)
- R – Reposition (optimize head position)
- S – Suction (suction mouth and nose)
- O – Open mouth (open the infant's mouth)
- P – Pressure increase (increase ventilation pressure)
- A – Airway alternative (alternative airway: laryngeal mask, intubation)
Step 3: Chest Compressions
If the heart rate remains below 60/min despite 30 seconds of effective ventilation, begin chest compressions.
Technique:
- Two-thumb technique (preferred): Both thumbs placed side by side or one on top of the other on the lower third of the sternum, hands encircling the thorax. This technique generates higher coronary perfusion pressure than the two-finger technique.
- Compression depth: Approximately one-third of the anterior-posterior chest diameter
- Compression-to-ventilation ratio: 3:1 (different from the PALS algorithm for older children at 15:2!). The 3:1 ratio reflects the fact that neonatal bradycardia is almost always respiratory in origin.
- Coordination: "One – and – two – and – three – and – breathe" yields 90 compressions and 30 breaths per minute = 120 events/min
Increase FiO₂ to 100% when chest compressions are initiated – regardless of the previous setting.
Step 4: Epinephrine and Vascular Access
If the heart rate remains below 60/min after 60 seconds of coordinated compressions and ventilation, epinephrine is indicated.
Epinephrine Dosing (Neonatal):
| Route of Administration | Dose | Dilution |
|---|---|---|
| Intravenous (preferred) | 0.01–0.03 mg/kg | 1:10,000 (= 0.1 mg/ml) |
| Endotracheal (if no IV access) | 0.05–0.1 mg/kg | 1:10,000 |
- Preferred access route: Umbilical vein (vena umbilicalis) – fast, technically easier than peripheral venipuncture in the neonate
- Umbilical venous catheter (UVC): Insert until blood can be aspirated (usually 2–4 cm from skin level); do not advance too deep (risk of hepatic vessel malposition)
- Intraosseous access: Alternative when UVC placement is not possible
- Endotracheal administration: Only as a bridge until vascular access is established. Absorption is unreliable, hence the higher dose.
Repeat: Epinephrine may be repeated every 3–5 minutes.
Step 5: Volume and Special Measures
If hypovolemia is suspected (e.g., placental abruption, vasa previa hemorrhage, fetomaternal transfusion):
- Volume bolus: 10 ml/kg isotonic saline or O Rh-negative packed red blood cells over 5–10 minutes IV
- May be repeated; caution regarding volume overload in preterm infants
Special Situation: Persistent Bradycardia Despite Correct Resuscitation
If all algorithm steps have been performed correctly and bradycardia persists, reversible causes must be systematically excluded. Based on the "Hs and Ts" of the PALS algorithm:
Hs:
- Hypoxia (Is ventilation adequate? Pneumothorax?)
- Hypovolemia (Hemorrhage? Umbilical cord complication?)
- Hypothermia (Measure temperature!)
- Hypoglycemia (Check blood glucose!)
- Hyperkalemia/metabolic disturbance (Blood gas analysis!)
- H⁺ (Acidosis)
Ts:
- Tamponade (with central line in situ or pericardial effusion)
- Tension pneumothorax (unilaterally diminished breath sounds, signs of shock)
- Toxins (maternal medications – take a history!)
In congenital complete (third-degree) AV block, even correctly performed resuscitation will only inadequately increase the heart rate. In this case, temporary pacing and early consultation with pediatric cardiology are essential.
Special Considerations in Preterm Infants
Preterm infants are particularly susceptible to bradycardia. So-called "apnea-bradycardia-desaturation episodes" (ABD episodes) are among the most common events in neonatal intensive care units.
- Immaturity of the respiratory center leads to central apneas
- Lower functional residual capacity accelerates desaturation
- Thinner chest wall requires careful titration of ventilation pressures
- Increased vulnerability to IVH with blood pressure fluctuations – therefore perform resuscitation measures thoughtfully but decisively
- Caffeine citrate is the standard prophylaxis for apnea-bradycardia episodes in preterm infants – loading dose 20 mg/kg IV, maintenance dose 5–10 mg/kg/day
Common Errors and Pitfalls
Analysis of neonatal resuscitations reveals recurring sources of error:
- Delayed initiation of PPV – tactile stimulation is continued too long while the heart rate continues to drop
- Ineffective mask ventilation – inadequate mask seal is the most common cause of ventilation failure. It is better to work through MR SOPA early rather than starting chest compressions with insufficient ventilation
- Wrong compression-to-ventilation ratio – 3:1 for neonates, not 15:2 (PALS) or 30:2 (adults)
- Delayed vascular access – umbilical venous catheterization should be prepared early, even if it is (hopefully) not needed
- Overlooking reversible causes – pneumothorax and hypothermia in particular are easily missed under stress
- Epinephrine dosing errors – confusion between dilutions (1:1,000 vs. 1:10,000) can be fatal. Always use 1:10,000 for neonatal resuscitation
Documentation and Team Communication
Structured resuscitation requires clear role assignments and communication. According to current recommendations, the team should fill at least the following roles:
- Team leader – coordinates, gives instructions, maintains situational awareness
- Airway – responsible for mask ventilation/intubation
- Compressions – performs chest compressions
- Access/Medications – UVC placement, preparing and administering medications
- Documentation/Timekeeper – records times, provides time announcements
Closed-loop communication (instruction – acknowledgment – confirmation) has been shown to reduce errors and is a central element of modern team-based resuscitation.
Practical Training
Neonatal bradycardia is a time-critical emergency where the algorithm must be second nature before you need it. Theory alone is not enough – the coordination of mask ventilation, chest compressions in a 3:1 ratio, and umbilical venous catheterization requires regular hands-on training under realistic conditions. In the PALS course from Simulation Tirol, you train exactly these scenarios in small groups using high-fidelity simulators, with structured debriefing and direct feedback. This way, you gain the confidence you need when the first minutes of a life are at stake.
Want to practice this hands-on?
In our PALS-Kurs (Pediatric Advanced Life Support) you practice this topic hands-on with high-tech simulators and experienced instructors.
More Articles
Airway Management in Neonates: Suctioning and Stimulation
When and how suctioning is indicated in neonates, tactile stimulation as the first step, and common errors in initial respiratory support. A practical guide for healthcare professionals in the delivery room and prehospital setting.
Broselow Tape and Weight Estimation in Pediatric Emergencies
In pediatric emergencies, medications must be dosed based on weight. This article explains the use of the Broselow Tape, alternative estimation formulas, and dosing aids for the most common emergency medications in pediatrics.
Dehydration in Children: Severity Grading and Rehydration
Assessing the degree of dehydration in infants and young children is an essential pediatric emergency skill. This article covers clinical signs, oral vs. intravenous rehydration, bolus administration, and electrolyte monitoring.

